women's health

Understanding Genitourinary Syndrome of Menopause

Microsoft Office Stock Image

What is Genitourinary Syndrome of Menopause?

Genitourinary syndrome of menopause (GSM) describes a group of symptoms and physical changes that affect the genital, urinary, and sexual health of women during peri- and post-menopause. GSM is thought to affect over half of all women who are postmenopausal. However, it often goes underdiagnosed and undertreated. Women may find it difficult to discuss symptoms of GSM with their healthcare providers. To complicate matters, symptoms of GSM look like those of other genitourinary conditions which may lead to misdiagnoses and delays in treatment.

GSM is a chronic and progressive condition that affects the lower urinary tract, vagina, and vulva. During perimenopause and after menopause, there are declining levels of estrogen and androgen in the genitourinary tract. This hormonal shift leads to physical changes and atrophy of vaginal, valvular, bladder, and urethral tissues. Physical changes and symptoms often reduce quality of life. Symptoms of GSM are progressive and worsen if left untreated.

During menopause, the ovaries stop producing estradiol. This results in a 95% decline in estradiol, a form of estrogen. Estrogen plays a key role in maintaining the elasticity, moisture, and blood flow of the tissues of the vagina, vulva, bladder, and urethra. A decline in estrogen leads to vaginal and urogenital atrophy. Vaginal secretions and lubrication are also reduced leading to vulvovaginal dryness and painful intercourse.

Estrogen also maintains a healthy, balanced, vaginal flora. It supports the growth of lactobacilli, which creates an acidic environment that protects the vagina and urinary tract from infections. When estrogen levels fall, lactobacilli decrease, vaginal pH rises, and the risk of infection increases.

While GSM is often associated with natural menopause, it is important to note that other conditions can also lower estrogen levels. Surgical menopause or oophorectomy, chemotherapy, primary ovarian insufficiency, and hypothalamic amenorrhea can contribute to decreased hormone levels and onset of GSM symptoms.

Quality of Life

GSM does not just affect the body. It can take a toll on a person’s emotional, psychological, and social well-being. It can lead to depression, anxiety, lowered self-esteem, and negatively impact personal relationships. Often, patients don’t seek help because they think their symptoms are a natural part of aging or they feel too embarrassed to talk to their provider.

Sexual symptoms of GSM like dyspareunia (painful intercourse) and decreased libido (sexual desire) often cause people to avoid intimacy out of frustration or embarrassment. As a result, their partners can feel rejected or confused, putting strain on the relationship.

Physical changes to the genital area such as vaginal dryness or loss of elasticity, may result in women having a poor body image or lowered self-esteem. They may feel ashamed about their body or feel they are losing their womanhood.

Urinary symptoms may cause emotional and social distress. Urgency or incontinence in public can lead to embarrassment or avoidance of social situations. Women may avoid exercise for fear of leakage.

2025 Guidelines

The term genitourinary syndrome of menopause was first used in 2014. However, since that time, there has been little guidance on how to define or diagnose it. In 2025, the American Urological Association released formal GSM guidelines titled Genitourinary Syndrome of Menopause: AUA/SUFU/AUGS Guideline (2025). These guidelines aim to improve quality of life for patients with GSM while optimizing symptom control. The guidelines provide information to healthcare providers on the identification and diagnosis of GSM. The guidelines also discuss how to counsel patients and provide treatment options for GSM.

“One of the most rewarding parts of my clinical practice has been helping patients improve their quality of life by addressing symptoms of GSM. Through scientific evidence and the application of shared decision making, this AUA guideline will help clinicians educate, empower, and treat patients with GSM.”

– Dr. Una Lee, vice-chair of the GSM guidelines

The guidelines emphasize a patient-centered approach to treating GSM that focuses on shared decision-making between patient and provider. Providers should understand the patient’s treatment goals and preferences. Education on symptoms, diagnosis, and treatment options is paramount.

Diagnosis

Diagnosis of GSM encompasses a physical examination, collecting a thorough patient history, and a careful review of symptoms.

Patients should be screened for GSM symptoms. It is important for providers to lead the patient through a thorough screening of symptoms because patients may be reluctant to discuss symptoms or bring up symptoms on their own. Providers should reassure patients that symptoms are common. Providers should understand which symptoms are most bothersome to the patient.

A focused history of GSM symptoms should be collected. It is important to understand when symptoms started, the severity of symptoms, and whether the symptoms affect the patient’s quality of life.

A pelvic exam helps confirm signs of GSM, such as tissue atrophy or physical changes. The physical exam should look for the presence of other conditions to ensure differential diagnoses are treated appropriately.

Treatment

Treatment for GSM should be tailored to the goals and preferences of individual patients. When discussing treatment options, providers should clearly explain both risks and benefits.

In the treatment of GSM, the use of natural or herbal supplements is not recommended. The FDA does not regulate these supplements. Their quality and formulations may be variable, making their effects and risks not generally predictable. In addition, there is little scientific data available to support the use of supplements.

Patients should be advised to avoid the use of soap or cleansers that may cause irritation and increase the symptoms of GSM.

Follow-up is essential. Providers should check in regularly to assess whether the treatment is working or if adjustments are needed. Since GSM is progressive, treatment may need to be modified over time.

Conclusion

Genitourinary syndrome of menopause is common, often distressing, and frequently underdiagnosed. By raising awareness and educating patients, providers can create a safe space for open discussion. This can lead to timely diagnosis, effective treatment, and an overall improvement in quality of life.

Terese H., APPE Student

Resources

  1. Kaufman MR, Ackerman LA, Amin KA, et al. The AUA/SUFU/AUGS Guideline on Genitourinary Syndrome of Menopause. J Urol. 0(0). doi:10.1097/JU.0000000000004589. https://www.auajournals.org/doi/10.1097/JU.0000000000004589
  2. American Urological Association. American Urological Association Releases New Guideline on Genitourinary Syndrome of Menopause. 28 Apr. 2025, American Urological Association, www.auanet.org/about-us/media-center/press-center/american-urological-association-releases-new-guideline-on-genitourinary-syndrome-of-menopause. Accessed 27 Aug. 2025.
  3. Carlson K, Nguyen H. Genitourinary Syndrome of Menopause. [Updated 2024 Oct 5]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2025 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK559297/

Understanding Genitourinary Syndrome of Menopause Read More »

Polycystic Ovary Syndrome: An Unseen Struggle for Many Women

Reference Image: Freepik

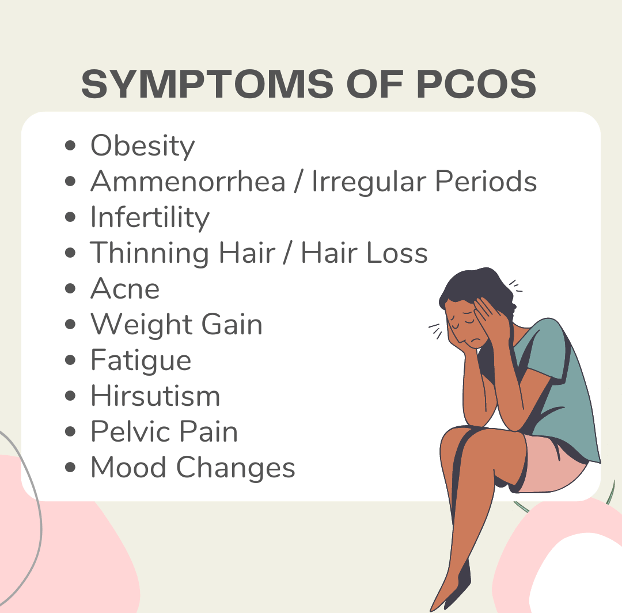
Despite affecting 1 in 10 women of childbearing age, polycystic ovary syndrome (PCOS) remains a common endocrine condition with many unanswered questions. While the disorder can significantly impact a woman’s health and fertility, it’s often under-recognized and misdiagnosed. A 2017 study highlights that over 50% of women with PCOS faced frustrating delays in diagnosis, sometimes over two years and involving more than three healthcare professionals. This leaves many undiagnosed women with ongoing concerns about managing symptoms like weight gain, irregular menstrual cycles, and infertility. Therefore, Increasing awareness and education among healthcare providers and improving patient support are crucial for enhancing outcomes and quality of life for those affected.

Image created with Canva

In addition to a myriad of symptoms, PCOS is linked to many other serious health risks that can further complicate a woman’s well-being. These include:

  • Type 2 Diabetes
  • Hypertension
  • Lipid abnormalities
  • Cardiovascular disease
  • Obesity
  • Sleep Apnea
  • Depression
  • Anxiety
  • Endometrial Cancer

Diagnosis

Most women find out they have PCOS in their 20s and 30s when they have concerns with fertility and visit their healthcare provider. However, PCOS can present at any age after puberty. To properly diagnose PCOS, a woman must have two of the following symptoms:

  • Irregular periods
  • Elevated androgen levels
  • Multiple cysts on one or both ovaries

Diagnosis typically involves several evaluations:

  • Physical exam → includes measuring blood pressure, body mass index (BMI), and checking for symptoms such as excessive hair growth or hair loss
  • Pelvic ultrasound (sonogram) → examines ovaries for cysts and the endometrial lining of the uterus
  • Blood test → check androgen hormone levels, lipids, thyroid function to rule out other causative factors, and A1c and blood glucose levels
  • Family history → the risk of PCOS is typically higher if an immediate family member, such as a sister, mom, aunt, also has a diagnosis

Cause

The exact cause of PCOS is not known, although several factors are thought to contribute. These include:

  1. Elevated levels of androgens

Elevated androgen levels can disrupt the ovarian cycle, leading to issues like anovulation (the absence of egg release), excessive hair growth, and acne

  1. Insulin resistance

Many women with PCOS do not respond properly to insulin and as a result, blood glucose is not absorbed efficiently within the body. This can increase glucose levels and over time increase the risk of type 2 diabetes.

Treatment

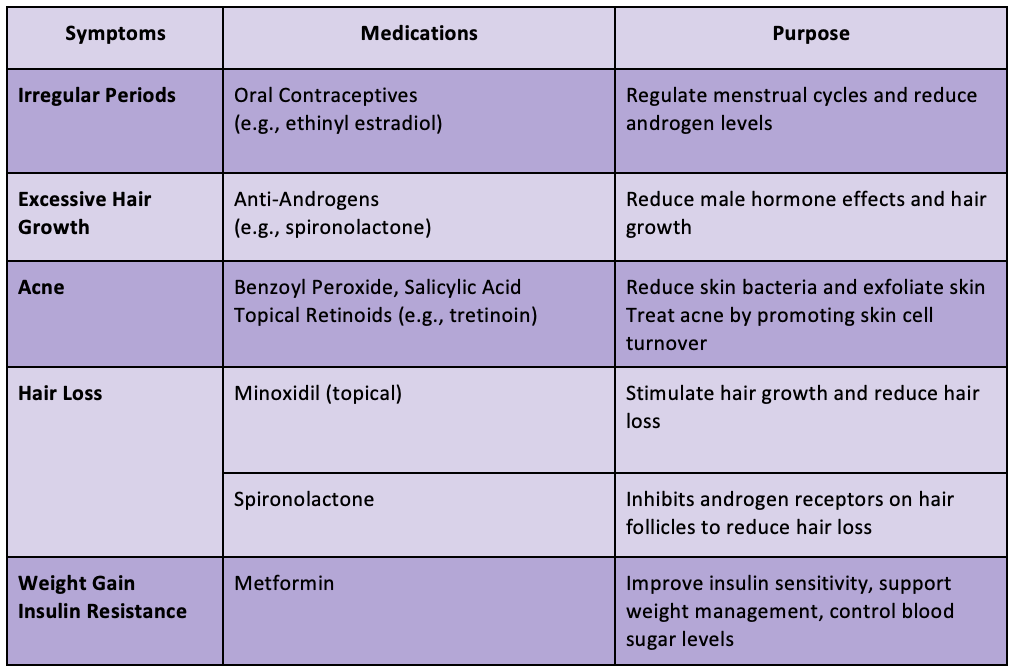
There is currently no cure nor any FDA-approved medications to treat PCOS. Symptoms are often managed through lifestyle interventions such as weight management, exercise, diet changes, or medications. See below for a comprehensive list of PCOS symptoms along with common first line off-label medication options.

Research and the Need for Action

Despite affecting 5 million women, PCOS remains severely underfunded and under-researched. Women with PCOS need treatments that address the condition’s root causes, not just its symptoms. Currently, only $10 million is allocated for PCOS research in 2024, and it is not included in recent major health funding initiatives. Consequently, this limited investment hinders the development of effective treatments.

There is hope, though. Spruce Biosciences is conducting the P.O.W.E.R study to assess if an investigational drug, tildacerfont, can effectively decrease androgen hormone production and improve PCOS symptoms. If successful, such breakthroughs could not only advance treatment options but also stimulate further research by demonstrating the condition’s relevance and significant impact on women’s health. With increased funding, these advances could significantly improve management and quality of life for those affected.

To conclude, PCOS remains a complex condition that is not completely understood. With its prevalence in women of childbearing age, it is only logical to push for more research in order to deepen our understanding and improve treatment options. Therefore, healthcare providers bear a responsibility to advocate for their patients to drive forward progress. By amplifying the voices of PCOS patients, we can drive meaningful change and improve outcomes for millions of women.


Winnie Chu

RxPharmacist Team

Resources

  1. Recommendations from the 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome. Fertility and Sterility. Available at: https://www.fertstert.org/article/S0015-0282(23)00719-7/fulltext. Accessed August 3, 2024.
  2. Polycystic Ovary Syndrome (PCOS). U.S. Department of Health and Human Services. Available at: https://www.womenshealth.gov/a-z-topics/polycystic-ovary-syndrome. Accessed August 3, 2024.
  3. Diabetes and Polycystic Ovary Syndrome (PCOS). Centers for Disease Control and Prevention. Available at: https://www.cdc.gov/diabetes/risk-factors/pcos-polycystic-ovary-syndrome.html. Accessed August 3, 2024.
  4. Delayed Diagnosis and a Lack of Information Associated With Dissatisfaction in Women With Polycystic Ovary Syndrome. The Journal of Clinical Endocrinology & Metabolism. 2017;102(2):604-612. Available at: https://academic.oup.com/jcem/article/102/2/604/2972079. Accessed August 3, 2024.
  5. Polycystic Ovary Syndrome (PCOS) Research Program. Icahn School of Medicine at Mount Sinai. Available at: https://icahn.mssm.edu/research/pcos. Accessed August 3, 2024.
  6. P.O.W.E.R. Study. Spruce Biosciences. Available at: https://sprucebio.com/power/. Accessed August 3, 2024.

Polycystic Ovary Syndrome: An Unseen Struggle for Many Women Read More »

Contraceptive Options for Contraindicated Patients

In 2015-2017, it was estimated 64.9% of women in the United States between the ages of 15-49 were using some form of contraception.1 The National Survey of Family Growth (NSFG) reported female sterilization (18.6%), oral contraceptive pills (12.6%), long-acting reversible contraceptives (10.3%) and male condoms (8.7%) were the most popular and common options, however, the degree of usage for each varied largely by age.1 Although some methods of contraception are far more efficacious than others, it is important to also take into consideration other factors such as demographics, side effects, duration, reversibility, and contraindications when offering contraceptive counseling. Likewise, dual protection should always be considered to prevent risks from HIV and STIs since even highly effective methods of contraception such as Intrauterine Device (IUDs) or surgical sterilization do not protect against these infections.2

Contraceptives can be grouped into hormonal and non-hormonal categories. See the interactive diagrams above which compare typical effectiveness per contraceptive method alongside their degree of hormonal properties. Although there are many options to choose from, some patients may find themselves contraindicated for hormonal contraceptives, specifically estrogen. The CDC provides a helpful summary chart (U.S. Medical Eligibility Criteria for Contraceptive Use) which outlines a comprehensive medical eligibility criteria across four categories of severity for several potential conditions and sub conditions.3 For women who find themselves in category 3, it would be wise to consider alternative birth control methods.

Women who find themselves in category 4 are completely contraindicated, typically due to hormonal therapy associated with estrogen releasing products. Patients contraindicated to hormone birth control methods can consider the above options which either circumvent hormones altogether or rely on progestin alone. Note when considering birth control methods, it is important to tailor the best option to the patient. For example, if a patient is looking to space their children out evenly across 3 years, a Nexplanon implant might be a good option. Likewise, a patient who is no longer interested in having children may be better suited for more permanent methods such as sterilization or a long-term IUD.

References

  1. Centers for Disease Control and Prevention. Current Contraceptive Status Among Women Aged 15–49: United States, 2015–2017. Accessed March 1, 2021. https://www.cdc.gov/nchs/products/databriefs/db327.htm.
  2. Centers for Disease Control and Prevention. Contraception. Accessed March 1, 2021. https://www.cdc.gov/reproductivehealth/contraception/index.htm.
  3. Centers for Disease Control and Prevention. US Medical Eligibility Criteria (US MEC) for Contraceptive Use, 2016. Accessed March 1, 2021. https://www.cdc.gov/reproductivehealth/contraception/mmwr/mec/summary.html.

Contraceptive Options for Contraindicated Patients Read More »

error: Content is protected !!
Popup Form

Want to get a free MPJE® or NAPLEX® cheat sheet? Subscribe to our email list!

By subscribing to this email list, you agree to our Privacy Policy and consent to receive emails from us.

MPJE® is a registered trademark of the National Association of Boards of Pharmacy. RxPharmacist®, LLC. and its services are neither affiliated with nor endorsed by the NABP®. None of the trademark holders is affiliated with, and does not endorse RxPharmacist’s product/site.

0